RAHWAY, NEW JERSEY, AND CAMBRIDGE, MASSACHUSETTS: An experimental personalised melanoma vaccine has reduced the relative risk of cancer recurrence or death by 42% when combined with immunotherapy after surgery. The Phase 3 trial involved 1,137 patients with high-risk melanoma.
The results offer hope for patients whose cancer may return after treatment. However, the vaccine remains investigational, and further research must establish its long-term benefits and safety.
How the Personalized Melanoma Vaccine Works
Melanoma is a type of skin cancer that develops in melanocytes, the cells that produce skin pigment. It can spread to nearby lymph nodes and distant organs, making treatment more difficult.
Intismeran, also known as V940 or mRNA-4157, is an experimental personalized cancer vaccine developed by Moderna and Merck, known as MSD outside the United States. Unlike preventive vaccines, it is designed to help treat existing cancer and reduce the risk of recurrence after surgery.
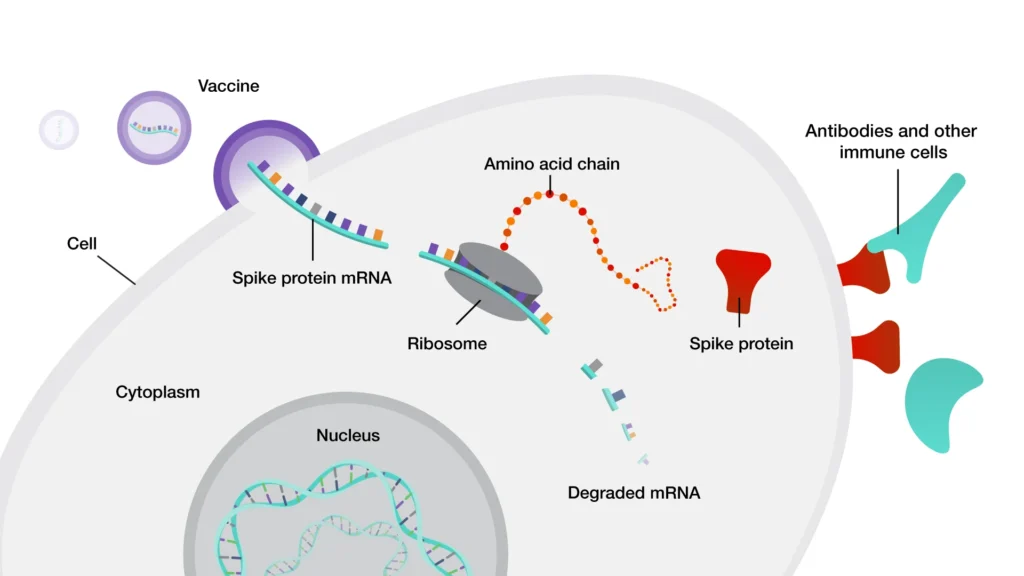
The vaccine uses genetic information from a patient’s tumor to identify mutations that produce abnormal proteins called neoantigens. Scientists use this information to design an individualized mRNA treatment that trains the immune system to recognize these cancer-specific targets.
The vaccine is being tested alongside pembrolizumab, an immunotherapy medicine marketed as Keytruda. Pembrolizumab blocks the PD-1 immune checkpoint, helping immune cells recognize and attack cancer cells.
The combination has two distinct roles. The vaccine helps the immune system recognize tumor-specific targets, while pembrolizumab helps maintain the immune response against cancer.
The Daily Mail also covered the development in its report, World-first skin cancer vaccine (Daily Mail, 2026). The headline requires careful interpretation: the trial demonstrated a 42% reduction in the relative risk of recurrence or death, not a 42% reduction in deaths alone.
What the Phase 3 Trial Found
The international INTerpath-001 trial evaluated intismeran in 1,137 patients with high-risk stage IIB to IV melanoma. Their cancer had been completely removed through surgery, but they remained at risk of recurrence.
Researchers randomly assigned participants to two groups. One group received intismeran alongside pembrolizumab, while the other received a placebo alongside pembrolizumab. Both groups received immunotherapy for approximately one year.
The trial assessed whether adding the personalized vaccine improved recurrence-free survival and distant metastasis-free survival.
Recurrence or Death Risk Fell by 42%
After a median follow-up of 24.6 months, the combination reduced the relative risk of recurrence or death by 42% compared with pembrolizumab alone.
The two-year recurrence-free survival rates were:
- 82.2% among patients receiving the vaccine combination.
- 70.0% among patients receiving pembrolizumab alone.
This is an absolute difference of 12.2 percentage points. In the trial, approximately 12 more patients per 100 in the combination group were alive without a recurrence at two years compared with the control group.
These percentages describe the results across the study groups. They do not predict an individual patient’s outcome.
Risk of Cancer Spreading Fell by 38%
The combination also reduced the relative risk of distant metastasis or death by 38%.
Distant metastasis occurs when cancer spreads from its original location to other parts of the body. Preventing this spread is an important goal because advanced melanoma can affect organs such as the lungs, liver and brain.
The two-year distant metastasis-free survival rates were 88.5% with intismeran plus pembrolizumab and 80.2% with pembrolizumab alone.
The study sponsors reported statistically significant improvements in both main outcomes. However, overall survival data are not yet mature, and researchers are continuing to follow participants to determine whether the benefits persist and whether the combination helps patients live longer. (Merck & Moderna, 2026)
Why This Cancer Vaccine Is Different
Traditional vaccines usually train the immune system to prevent an infection. A therapeutic cancer vaccine works differently because it is designed to help the immune system recognize cancer cells that are already present or may return.
Intismeran uses tumor-specific genetic information rather than a single vaccine formula for every patient. This individualized approach may help the immune system recognize targets that differ from one person’s cancer to another.
The treatment also builds on advances in mRNA technology used in COVID-19 vaccines. However, a cancer vaccine requires a different design and purpose from an infectious disease vaccine.
Developing each personalized dose requires analysis of the patient’s tumor and the preparation of a tailored vaccine. According to reporting by the Associated Press, the process from tumor analysis to vaccine preparation can take around six weeks or longer. The manufacturers have not announced a final price for routine treatment. (Neergaard, 2026)
Side Effects and Safety Findings
The potential benefits must be considered alongside the risks.
Treatment-related adverse events were reported in 95.8% of patients receiving intismeran with pembrolizumab, compared with 90.0% of patients receiving pembrolizumab alone. These figures include events attributed to the study treatments and do not mean that every patient experienced a severe reaction.
Common treatment-related adverse events in the combination group included:
- Fever, reported in 52.2% of patients.
- Injection-site pain, reported in 51.0%.
- Fatigue, reported in 38.5%.
More severe treatment-related adverse events, classified as Grade 3 to 5, occurred in 14.2% of the combination group and 13.4% of the control group.
These findings suggest that the combination can cause additional side effects, although the rates of severe treatment-related events were similar between the groups.
Patients receiving immunotherapy should report new or worsening symptoms to their oncology team because some immune-related complications require prompt medical assessment.
Is the Melanoma Vaccine Available Yet?
As of 24 October 2026, intismeran remains an investigational treatment rather than an approved routine therapy. Merck and Moderna have stated that they are engaging with regulatory authorities following the positive Phase 3 findings.
The results do not mean that the vaccine is available to all patients or that it has been established as a cure. Regulatory authorities must evaluate the evidence before deciding whether to approve it.
Cost and manufacturing capacity may also affect access. Each vaccine must be tailored to the genetic characteristics of the individual patient’s tumor, which requires specialized analysis and production.
Researchers are investigating personalized cancer vaccines in other tumor types, including kidney, bladder and lung cancer. However, the positive melanoma findings do not establish that the same approach will work for these other cancers.
Professor Alan Melcher of the Institute of Cancer Research, London, described the findings as an important proof of principle while emphasizing that longer follow-up is needed to understand the effect on overall survival. (Institute of Cancer Research, 2026)
How Physiotherapy Supports Melanoma Recovery
The vaccine is an oncology treatment, not a physiotherapy intervention. However, physiotherapy may support patients recovering from melanoma surgery or managing physical difficulties associated with cancer treatment.
The rehabilitation plan depends on the surgical procedure, wound healing, symptoms and the patient’s medical condition.
Regaining Movement After Surgery
Melanoma surgery may involve removing the affected skin and surrounding tissue. Some patients also need surgery involving nearby lymph nodes.
Depending on the procedure, recovery may involve pain, restricted movement or difficulty returning to everyday activities.
A physiotherapist can assess movement and functional limitations and develop an individualized program. Treatment may include gentle mobility exercises, progressive strengthening and a gradual return to normal activities.
Patients should follow their surgeon’s advice before starting exercises that place strain on a healing wound or skin graft.
Managing Cancer-Related Fatigue
Cancer and its treatment can contribute to fatigue, reduced muscle strength and lower exercise tolerance. These changes may make walking, household tasks and work more difficult.
A physiotherapist can help patients gradually rebuild strength, endurance and confidence with movement. Depending on their health and treatment status, a program may include walking, aerobic exercise, resistance training and pacing strategies.
The American Society of Clinical Oncology recommends aerobic and resistance exercise during active cancer treatment with curative intent to help reduce treatment side effects and preserve physical function. The evidence does not establish that exercise itself prevents cancer recurrence or improves survival. (Ligibel et al., 2022)
Recognizing Lymphoedema After Lymph Node Surgery
Some patients may develop lymphoedema after lymph nodes are removed or damaged during cancer treatment. This condition occurs when fluid builds up in body tissues and causes swelling.
The affected area depends on the location of the lymph node procedure. For example, surgery involving lymph nodes in the groin or armpit may affect fluid drainage from the nearby limb.
A trained lymphoedema professional can assess swelling and recommend appropriate management. Depending on the patient’s needs, this may include specific exercises, skin care and compression.
Not every patient develops lymphoedema. New or persistent swelling should be assessed by a healthcare professional rather than managed through unsupervised exercise. (American Cancer Society)

Conclusion
The personalized melanoma vaccine intismeran reduced the relative risk of recurrence or death by 42% when combined with pembrolizumab in a Phase 3 trial involving 1,137 patients with high-risk melanoma after surgery. The combination also reduced the risk of distant metastasis or death by 38%.
These findings mark an important development in personalized cancer treatment, but longer follow-up is needed to establish the effect on overall survival. Regulatory approval, cost and manufacturing capacity will also influence access.
For patients recovering from melanoma, specialist-led cancer treatment and follow-up remain essential. Individualized physiotherapy may help restore movement, strength and physical function after surgery, supporting recovery and quality of life.