


An ankle that keeps hurting after a seemingly ordinary sprain can sometimes be telling you something more complicated than a ligament injury.
One less commonly discussed possibility is osteochondritis dissecans of the ankle, usually involving the talus.
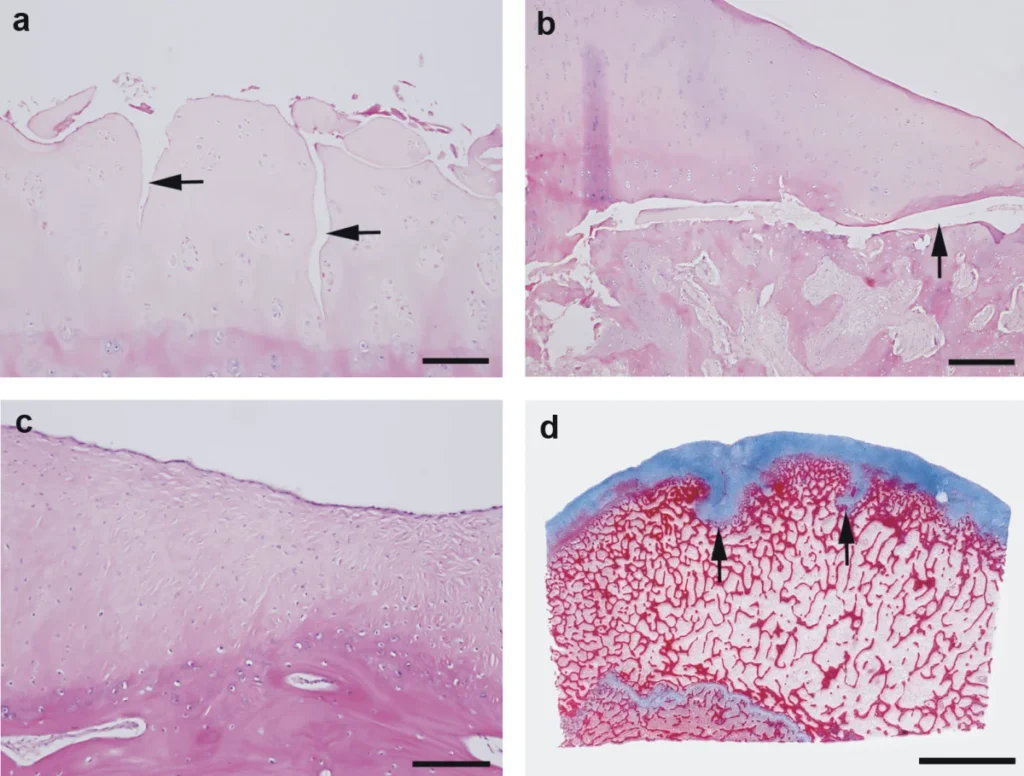
The condition affects the osteochondral unit, meaning the smooth cartilage covering the joint and the bone immediately beneath it.
Quick Answer
Osteochondritis dissecans of the ankle is an osteochondral injury usually affecting the talus, involving the joint cartilage and the bone underneath it. It can cause deep ankle pain, swelling after activity, stiffness, catching or difficulty returning to sport after an ankle injury. MRI is commonly used to assess the cartilage and underlying bone. Stable and minimally symptomatic lesions may be managed with activity modification and rehabilitation, while persistent symptoms, unstable fragments or larger lesions may require surgical treatment.
In modern literature, doctors often use the broader term osteochondral lesion of the talus (OLT) because these injuries exist on a spectrum, from subtle damage beneath intact cartilage to an unstable fragment that can separate inside the joint.
What makes this condition tricky is that the ankle may continue to look relatively normal from the outside.
You may have little swelling, no dramatic bruising and no obvious deformity, yet experience deep ankle pain, stiffness, catching or discomfort during weight-bearing.
And here is something I tell patients: persistent ankle pain after a sprain deserves reassessment when the recovery does not follow the expected pattern.
Not every painful ankle is an osteochondral lesion, but not every ankle problem is a ligament problem either.
Key Takeaways
- Osteochondritis dissecans of the ankle usually involves the talus and can affect both cartilage and underlying bone.
- A persistent ankle problem after a sprain should not automatically be blamed on a ligament injury.
- Deep pain, recurrent swelling, stiffness, catching or locking can be important clues.
- MRI can help evaluate cartilage, bone marrow changes, cysts and lesion stability.
- Not every osteochondral lesion requires surgery. Stability, size, depth, symptoms and patient factors matter.
- Physiotherapy focuses on appropriate loading, mobility, strength, balance and gradual return to activity.
- Postoperative rehabilitation varies considerably according to the procedure performed.
- Do not return to running or jumping simply because ordinary walking has become comfortable.
- Persistent mechanical symptoms or failure to progress should prompt reassessment.
What exactly is osteochondritis dissecans of the ankle?
The talus is the bone sitting between the lower leg and the foot.
A large portion of its surface participates in the ankle joint and is covered with articular cartilage, which allows the bones to move smoothly with very little friction.
An osteochondral lesion affects two layers:
- the articular cartilage
- the subchondral bone underneath it
Osteochondritis dissecans is traditionally used when there is a process involving the underlying bone that can progress toward separation of an osteochondral fragment.
The terminology can therefore be confusing.
A scan may say “osteochondral lesion,” “osteochondral defect,” “osteochondritis dissecans,” or “osteochondral injury of the talar dome.”
These terms are related but are not necessarily interchangeable in every clinical situation.
The important question is not simply, “Do I have a lesion?”
The more useful questions are:
Is the cartilage intact? Is the underlying bone stable? Is there a cyst? Is the fragment displaced? How large and deep is the lesion? And does it actually match the symptoms?
Current reviews emphasize that treatment should be individualized according to lesion and patient characteristics rather than applying one treatment to everyone. (Springer Link)
Why can an ankle sprain lead to this problem?
One of the lesser-known facts about osteochondral lesions is that they are frequently linked to trauma.
A forceful inversion or twisting injury can compress the talar dome against the tibia.
Instead of producing only ligament damage, the impact can injure the cartilage and the bone underneath.
This is one reason some people say:
“My ankle sprain healed, but my ankle never really became normal.”
The ligament may have recovered sufficiently for walking, while an osteochondral injury remains.
Reviews have estimated that a substantial proportion of talar osteochondral lesions are associated with trauma, particularly ankle sprains or fractures.
One widely cited review reported that up to 75% of OLTs may have a traumatic origin. (Bone & Joint Research)
However, trauma is not the only possible explanation.
Repetitive loading, microtrauma and other factors can also contribute.
That is particularly relevant to runners, dancers, jumping athletes and people whose ankles repeatedly absorb high impact.
The pain may not feel like a typical ankle sprain
This is where patients often become confused.
A lateral ankle sprain usually produces pain around the injured ligaments, often on the outside of the ankle.
An osteochondral lesion can feel deeper and harder to localize.
You may describe it as:
- deep ankle pain
- pain during weight-bearing
- discomfort with running or jumping
- pain after prolonged walking
- stiffness after inactivity
- swelling after activity
- catching or clicking
- a feeling that the ankle is “not moving smoothly”
- occasional locking
- pain that keeps returning after apparently successful sprain rehabilitation
Some people have surprisingly mild symptoms despite visible lesions on imaging.
Others have considerable pain despite a relatively small lesion.
That mismatch is important. The scan should not be interpreted independently of the person.
A 2023 German Society of Orthopedics and Traumatology recommendation specifically noted that initial symptoms and imaging alone cannot reliably predict whether conservative treatment will succeed. (Cartilage)
Osteochondritis dissecans ankle symptoms you should not ignore
1. Deep pain that persists after an ankle sprain
If your ankle still hurts weeks after a sprain, particularly when walking, running or loading the joint, it is reasonable to ask whether something beyond the ligament has been injured.
This does not mean every lingering sprain is an osteochondral lesion.
Tendon irritation, joint stiffness, instability, bone injury and altered movement can all produce persistent symptoms.
But failure to progress is clinically meaningful.
2. Pain with weight-bearing
The ankle is designed to tolerate considerable load, but an osteochondral defect may become painful when the talar dome is repeatedly compressed.
You might notice pain during:
- walking downhill
- running
- jumping
- climbing stairs
- prolonged standing
- single-leg exercises
3. Swelling after activity
Some people do not wake up with a visibly swollen ankle.
Instead, swelling appears after the joint has been loaded.
That pattern can be useful information during assessment.
4. Catching, clicking or locking
A feeling that the ankle briefly catches or does not glide normally deserves attention.
Mechanical symptoms become particularly important when there is concern about an unstable osteochondral fragment.
5. Reduced ankle movement
You may notice difficulty getting the knee forward over the toes, squatting deeply or descending stairs.
But reduced dorsiflexion does not automatically mean the cartilage is damaged.
Calf tightness, joint capsule restriction, pain inhibition and previous immobilization can all reduce movement.
6. Recurrent “sprains”
An osteochondral problem can coexist with ankle instability.
If someone repeatedly rolls the same ankle and never feels completely confident on it, the assessment should not stop at the lateral ligaments.
Can osteochondritis dissecans of the ankle heal on its own?
Sometimes, particularly in carefully selected patients.
But “healing” requires clarification.
A person may become pain-free even though the lesion remains visible on imaging.
Conversely, an imaging abnormality may change while symptoms do not improve.
This is one of the most interesting findings in the literature.
A 2023 systematic review of 30 studies involving 868 patients found an overall pooled clinical success rate of approximately 45% for non-operative treatment.
Radiological deterioration was relatively uncommon in the available studies, but the evidence was highly heterogeneous. (Springer)
The same review illustrates why patients should not assume that “conservative treatment” means simply resting for a few days.
It can involve carefully modifying activity, controlling loading, restoring movement and strength, and monitoring symptoms.
For children and adolescents, the situation can be different because open growth plates may influence healing potential.
How is osteochondritis dissecans of the ankle diagnosed?
Clinical assessment comes first
As a physiotherapist, I would not begin with the MRI report.
I would want to understand:
- how the injury occurred
- whether there was an inversion or twisting mechanism
- where the pain is located
- what activities reproduce it
- whether swelling appears immediately or later
- whether there is catching or locking
- whether the ankle feels unstable
- how walking has changed
- whether previous rehabilitation helped
- whether the patient returned to sport too quickly
The examination may include ankle range of motion, calf flexibility, single-leg balance, gait, strength and functional loading.
X-ray may be useful, but it is not the whole story
Plain radiographs can identify some osteochondral lesions and are useful for evaluating bone structure and other abnormalities.
However, an early or subtle lesion can be difficult to appreciate.
That is one reason persistent symptoms after an ankle injury sometimes require more advanced imaging.
MRI is particularly useful
MRI can provide information about:
- cartilage integrity
- bone marrow edema
- lesion depth
- subchondral cysts
- separation of a fragment
- surrounding bone changes
A radiology review notes that MRI has become an important tool for staging talar osteochondral lesions. (Journal of Belgian Society of Radiology)
CT has a different strength
CT can be especially helpful for understanding the bony architecture and lesion morphology.
MRI and CT should therefore not be thought of as competitors where one is always “better.”
They answer somewhat different questions.
The final imaging strategy depends on the clinical situation and the decision being considered.
Does the location of the lesion matter?
Yes.
The talar dome is not a perfectly uniform surface.
Lesions can occur medially or laterally, and their location, size, depth and stability influence treatment decisions.
A systematic review of 11,785 patients also highlighted an important research problem: lesion size and morphology have not always been reported consistently across studies. (Sage Journals)
This matters because you may see a headline online saying something like “microfracture works for lesions under X millimeters.”
That number should not be treated as an absolute rule for every patient.
A lesion’s depth, cystic changes, stability, location, symptoms, age, activity level and previous treatment all influence the decision.
Osteochondritis dissecans ankle treatment: what actually works?
Treatment generally falls into two broad categories:
non-operative management and surgery.
The decision should be individualized.
Conservative treatment
Conservative management may be appropriate when:
- symptoms are mild
- the lesion is stable
- there is no displaced fragment
- the patient can modify aggravating activity
- the clinical picture supports non-operative care
The goal is not simply to “rest the ankle.”
The goal is to reduce excessive joint stress while maintaining as much healthy movement and capacity as possible.
This may involve:
- temporary activity modification
- avoiding repetitive impact
- relative unloading when necessary
- restoring ankle mobility
- progressive calf and ankle strengthening
- balance and proprioception work
- hip and lower-limb strength
- gradual return to impact
- footwear modification where appropriate
- correction of major movement-control deficits
The 2023 DGOU recommendations emphasize adaptation of activity to the ankle’s functional capacity.
They also report that adult improvement with conservative management has been reported in roughly 45% to 59% of patients, while acknowledging limitations in the evidence. (Reasearch)
Physiotherapy is not about “healing cartilage with exercises”
This distinction is important.
I would never tell a patient that a few ankle exercises can magically regrow damaged cartilage.
Physiotherapy has a different role.
We can improve the environment around the injured joint.
That may mean improving:
- ankle mobility
- calf capacity
- lower-limb strength
- balance
- movement coordination
- walking mechanics
- tolerance to progressive loading
- confidence with single-leg activity
In other words, physiotherapy can help you load the ankle intelligently.
That is very different from claiming that physiotherapy alone can repair every osteochondral defect.
When is surgery considered?
Surgery becomes more relevant when symptoms persist despite appropriate conservative management, or when imaging demonstrates an unstable or displaced lesion.
A displaced osteochondral fragment is a very different situation from a small, stable lesion with mild symptoms.
The 2024 DGOU operative recommendations support bone marrow stimulation for selected smaller lesions without a significant bony defect, while larger lesions may require other cartilage or osteochondral restoration strategies. (Bio Scientifica)
Possible procedures include:
Arthroscopic debridement and bone marrow stimulation
The surgeon removes unstable or damaged tissue and creates small channels in the underlying bone to stimulate a healing response.
Microfracture is one form of bone marrow stimulation.
It is generally used for appropriately selected lesions rather than every osteochondral defect.
A systematic review and meta-analysis published in 2024 examined arthroscopic microfracture and associated techniques and found generally favorable clinical outcomes, although the evidence base still has limitations. (Elsevier)
Retrograde drilling
In selected lesions where the cartilage surface remains relatively intact, drilling can stimulate the underlying bone without deliberately breaching the cartilage surface.
This is a technically different approach and may be considered depending on lesion characteristics.
Osteochondral autograft transplantation
For selected larger or unsuitable lesions, an osteochondral graft may be transferred from another part of the patient’s body.
This replaces damaged cartilage and underlying bone rather than relying solely on a reparative response.
A systematic review in athletes reported an average return-to-play rate of approximately 86% after autologous osteochondral transplantation, although the authors emphasized the low quality of much of the available evidence. (WILEY)
Other cartilage restoration procedures
Depending on the lesion, surgeon expertise and country, treatment may include scaffolds, autologous chondrocyte procedures or other cartilage-repair strategies.
These are not interchangeable treatments.
The choice should be based on lesion size, depth, stability, bone involvement, previous procedures and patient goals.
The physiotherapy part people often underestimate
Whether treatment is conservative or surgical, rehabilitation matters.
After surgery, rehabilitation is not simply “wait until the bone heals.”
The ankle must progressively regain:
- controlled range of motion
- muscle strength
- weight-bearing tolerance
- balance
- walking quality
- impact tolerance
- sport-specific capacity
However, there is an important warning against copying someone else’s postoperative timeline.
A 2024 systematic review examined 227 articles and 255 postoperative rehabilitation protocols after different OLT procedures.
The researchers found substantial variation in weight-bearing, immobilization, range-of-motion and return-to-sport recommendations.
Only about one-quarter of protocols reported subjective or objective progression criteria. (ESSKA Journals)
That means the “six-week rule” you read online may not apply to your particular operation.
Your surgeon’s procedure and your lesion characteristics matter.
An interesting question: should you stay completely off the ankle after microfracture?
This is more nuanced than many patients realize.
Historically, prolonged non-weight-bearing was commonly prescribed after microfracture.
But research has challenged the assumption that longer non-weight-bearing is always better.
A prospective randomized trial found that early weight-bearing after microfracture produced better short-term functional scores at six weeks, while later outcomes showed no significant differences between early and delayed weight-bearing groups.
A separate systematic review and meta-analysis of five randomized trials also found comparable clinical outcomes between early and delayed weight-bearing approaches.
This does not mean you should start walking early after surgery without permission.
It means rehabilitation should be individualized rather than based on fear.
Things I would tell a patient to avoid
Do not repeatedly “test” the ankle with painful jumping
Painful impact does not prove that the ankle is becoming stronger.
Repeatedly provoking symptoms can make it difficult to determine whether the rehabilitation plan is working.
Do not assume every ankle click means cartilage damage
Clicking can occur for many reasons.
A click alone is not a diagnosis.
Painful catching or true locking is more concerning.
Do not chase MRI perfection
An MRI may remain abnormal even when you are functioning well.
Your symptoms, function and clinical examination matter.
Do not return to running simply because walking is pain-free
Running introduces substantially different loading demands.
A sensible progression may move through:
walking → brisk walking → strength → controlled hopping → repeated hopping → running drills → sport-specific work.
The exact progression depends on the lesion and treatment.
Do not ignore recurrent swelling
A repeatedly swollen ankle after activity deserves reassessment, particularly when the swelling is accompanied by deep pain or mechanical symptoms.
Things you can do to protect the ankle
If you have already been diagnosed with an osteochondral lesion, your goal should be to create a sustainable loading strategy.
Maintain general fitness through activities that your clinician considers appropriate.
Strengthen the calf progressively.
Do not neglect the hip and knee simply because the lesion is in the ankle.
Work on single-leg control when appropriate.
Wear footwear that provides a comfortable and predictable platform during the rehabilitation phase.
And perhaps most importantly, respect the difference between acceptable rehabilitation discomfort and worsening joint symptoms.
A physiotherapist can help you identify that difference.
When should you see an orthopaedic specialist?
Seek medical assessment if you have:
- persistent ankle pain after an injury
- recurrent swelling
- deep pain during weight-bearing
- catching or locking
- inability to return to normal activity
- repeated ankle injuries
- significant pain despite appropriate rehabilitation
- a known osteochondral lesion
- a suspected displaced fragment
Urgent assessment is particularly important after a significant injury with inability to bear weight, marked deformity, severe swelling, numbness or other concerning symptoms.
Can osteochondritis dissecans cause ankle arthritis?
It can contribute to degenerative changes in some patients, particularly when a lesion is unstable, deep, cystic or associated with other joint damage.
But it is important not to frighten people unnecessarily.
The 2023 DGOU recommendations noted that patients with minimal symptoms are unlikely to experience progression to ankle osteoarthritis, while deeper lesions, subchondral cysts and greater bone marrow edema were identified as risk factors for progression. (PubMed)
The message is therefore not “osteochondritis dissecans inevitably becomes arthritis.”
The better message is:
A stable, minimally symptomatic lesion and an unstable, mechanically symptomatic lesion are not the same disease situation.
A lesser-known point: feeling better does not always mean the lesion has disappeared
This is particularly important for younger patients.
Research on juvenile osteochondritis dissecans of the talus has shown that symptoms can resolve before radiographic healing is complete.
In one study of skeletally immature patients, many children became asymptomatic despite persistent radiographic lesions.
[Research citation: juvenile osteochondritis dissecans study.]
This explains why follow-up cannot always be based solely on “It doesn’t hurt anymore.”
For a growing child or adolescent, the treating specialist may recommend follow-up imaging and activity restrictions even when symptoms improve.
Final word from a physiotherapist
Osteochondritis dissecans of the ankle is one of those conditions that can hide behind the much more familiar diagnosis of an ankle sprain.
The clue is often not dramatic pain.
It is the ankle that never quite gets back to normal.
Persistent deep pain, activity-related swelling, stiffness, catching or difficulty progressing back to running should not automatically be blamed on weak muscles or an old sprain.
At the same time, discovering an osteochondral lesion on MRI does not automatically mean you need surgery.
The most useful treatment decision considers the entire picture: your symptoms, age, activity level, lesion size and depth, cartilage stability, bone involvement, mechanical symptoms and response to appropriate conservative care.
From a physiotherapy perspective, my priority is to help you understand your ankle rather than fear it.
Protect the joint when it needs protection.
Restore the movement you can safely restore.
Build strength progressively.
Reintroduce impact gradually.
And if the ankle continues to behave differently from what your rehabilitation should predict, investigate rather than repeatedly pushing through it.
The goal is not merely to make the MRI look better.
The goal is to give you an ankle that is strong, predictable and capable of handling the life you want to live.
Osteochondritis Dissecans of the Ankle: FAQs
What is osteochondritis dissecans of the ankle?
It is an osteochondral problem that usually affects the talus, involving the articular cartilage and the bone underneath it. Modern medical literature often describes these injuries as osteochondral lesions of the talus.
What are the symptoms of ankle osteochondritis dissecans?
Symptoms can include deep ankle pain, activity-related swelling, stiffness, pain with weight-bearing, catching, clicking, locking and difficulty returning to running or sports.
Can a sprained ankle cause an osteochondral lesion?
Yes. Twisting and inversion injuries can damage the talar dome and may produce an osteochondral lesion in addition to ligament injury.
Is MRI needed to diagnose an osteochondral lesion?
MRI is commonly used because it can evaluate cartilage, the underlying bone, bone marrow changes, cysts and lesion characteristics that may not be obvious on a plain X-ray.
Can osteochondritis dissecans of the ankle heal without surgery?
Some stable lesions can improve with conservative treatment, particularly when symptoms are mild and activity can be appropriately modified. However, conservative treatment does not work for everyone.
What physiotherapy is used for an osteochondral lesion?
Depending on the condition, physiotherapy may include ankle mobility work, calf and lower-limb strengthening, balance training, movement retraining and a gradual progression of weight-bearing and impact.
When does an ankle osteochondral lesion need surgery?
Surgery may be considered for persistent symptoms despite appropriate conservative treatment, unstable lesions, displaced fragments or lesions whose size and characteristics make non-operative treatment less suitable.
Can osteochondritis dissecans lead to ankle arthritis?
Some lesions can contribute to degenerative changes, particularly when they are deep, cystic or unstable. However, a stable, minimally symptomatic lesion does not automatically progress to ankle arthritis.
Stay tuned with us for more health related topics.
Follow us on LinkedIn and Instagram for more.
More Read






Medical Disclaimer!
This article has been reviewed and written under the guidance of our Head Physiotherapist, Dr. Kruti Raj (PT, MUHS,CPT,CMPT). The information shared is intended for educational purposes only and should not be considered a substitute for personalized medical advice, diagnosis, or treatment.
Please consult us or any other qualified healthcare professional before beginning any exercise program, especially if you are experiencing pain, recovering from injury, or managing a medical condition.



